
One night of recording tells you what happened that night. VTP™ is how we find the appliance setting that actually suits you: a ring worn at home for weeks, a journal each morning, and a report that compares every setting against your own baseline nights. It is a method for measuring, not a treatment in itself.
Why one night misleads
The same person, on the same setting, does not sleep the same way twice. In one of the records below, breathing disturbance ran between 1.9 and 5.1 events an hour across twenty-three nights with nothing changing. In another, hypoxic burden on a single fixed setting ranged from 8 to 39. A one-night study lands somewhere in that spread and gets reported as the answer. Averages across several nights at each setting, with the outliers named and set aside, are what let you tell a setting that helps from one that merely had a good night.
How it works
- Baseline nights first. You wear the ring for several nights before anything changes: with no appliance, or on whatever you are using now. That becomes the yardstick everything else is measured against.
- One setting at a time, several nights each. Dr. Bishara sets the appliance; you wear it and record. Nothing is judged on a single night, and you do not change the setting on your own.
- Your journal each morning. One line a day: what you wore, how your jaw feels (green, amber or red), and if you keep a home cuff, your blood pressure on waking. Where the journal and the automated record disagree about what was worn, the journal governs.
- The comparison. Every setting is compared on hypoxic burden, breathing disturbance, lowest oxygen, heart rate through the night, sleep quality, fragmentation and sleep length, against your own baseline. Nights under four hours are left out; nights with a fever or an obvious one-off are set aside and said so.
- The report goes to you and your physician. Plain language, every term explained, the same document to both. It informs a shared decision; it is not a diagnosis and does not replace a physician-ordered study.
What the records have taught us
Four completed records, each shared with the patient’s permission and with names, dates and personal details removed. Nights are numbered in order. None of these is a diagnosis; each is what the nights showed and what that changed.
Case A — thirty nights, five settings: wearing it mattered, advancing it did not
The question. An adult with mild-to-moderate breathing disturbance, advanced step by step from 0 to 3.5 mm. The expectation was that each step forward would buy more improvement.
What the nights showed. Hypoxic burden fell from a median of 45.0 on untreated nights to 28.1 on appliance nights, a 38% reduction that held up to formal statistics (p = 0.005). Across the five settings there was no dose-response at all: every setting from 0.0 upward delivered essentially the same benefit. The only thing that changed at 3.5 mm was comfort: nineteen green mornings at the lower settings, then four amber ones, with a headache, a 3:45 a.m. waking and a sore jaw. Stepping back down went straight to green. The journal also caught four nights the automated record had wrong, including one where the patient had tried 4.0 mm, could not swallow, and slept without the appliance.
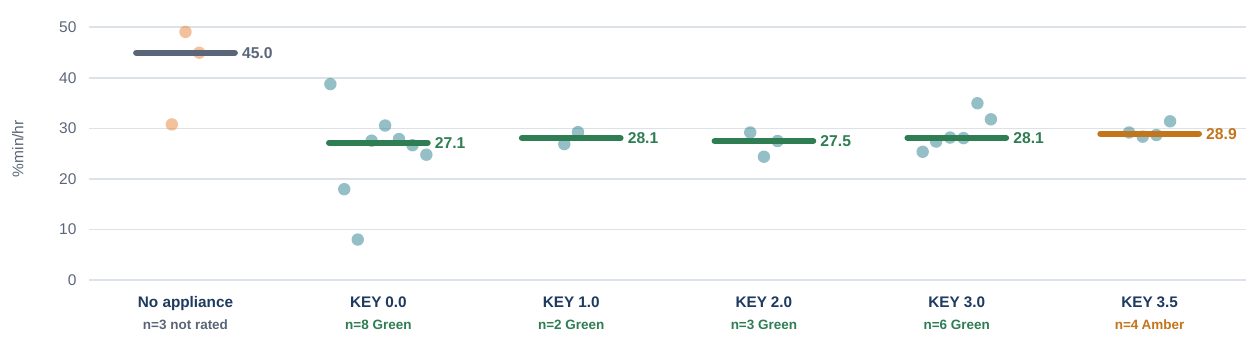
Every night at each setting, medians marked. The untreated column separates; the five appliance columns do not. That flat profile is the finding.
What it changed. The setting went back to where the jaw was comfortable. The report to the sleep physician said plainly that the appliance had helped a lot and had not finished the job, and that the next step was more likely something alongside it than more advancement.
Case B — seventeen nights, severe numbers: advancing the setting made the averages worse
The question. An adult with severe breathing disturbance (baseline around 40 events an hour, hypoxic burden in the sixties), moved from 0 to 1.0 to 2.0 mm over fourteen appliance nights.
What the nights showed. Setting 0.0 was the only one that beat the patient’s own baseline (33 events an hour and burden 47 against 41 and 64). Settings 1.0 and 2.0 ran at or above baseline, and sleep quality was lowest at 2.0. Inside the three nights at 2.0 there was a steady improvement night to night, which is exactly the kind of thing a single night would either miss or overstate.
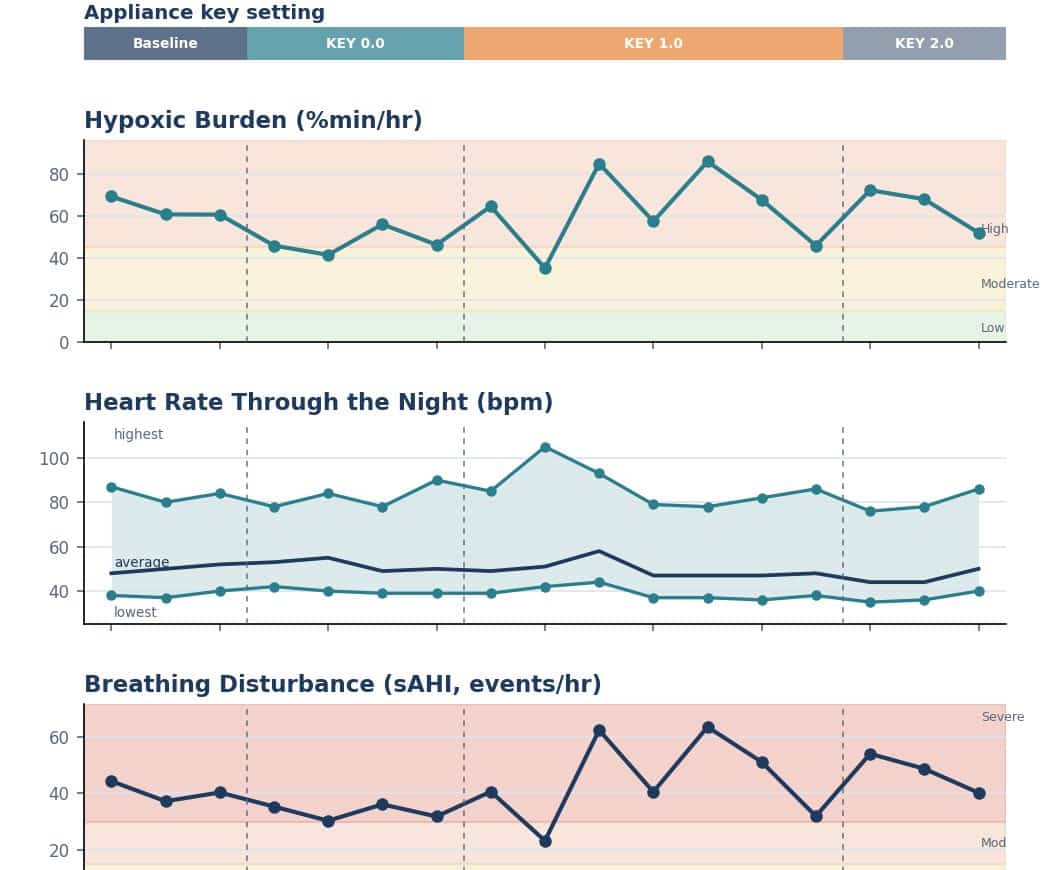
Hypoxic burden, heart rate and breathing disturbance across the setting bands. The numbers do not fall as the setting advances.
What it changed. The comparison put a clear question in front of Dr. Bishara and the patient’s physician: at these numbers, whether an appliance on its own is the right tool, and which setting deserves more nights before deciding.
Case C — twenty-four nights on someone else’s appliance: not an airway problem
The question. An adult already wearing an oral appliance made elsewhere, with no record of its settings, who still slept badly. The record describes sleep on that appliance rather than any adjustment of it.
What the nights showed. Breathing and oxygen were reassuring on almost every night. Sleep quality and continuity were far outside the expected range on every single night, without exception, and a repeating, wave-like breathing rhythm (periodicity) showed up on most nights at levels well above the 2% expected.
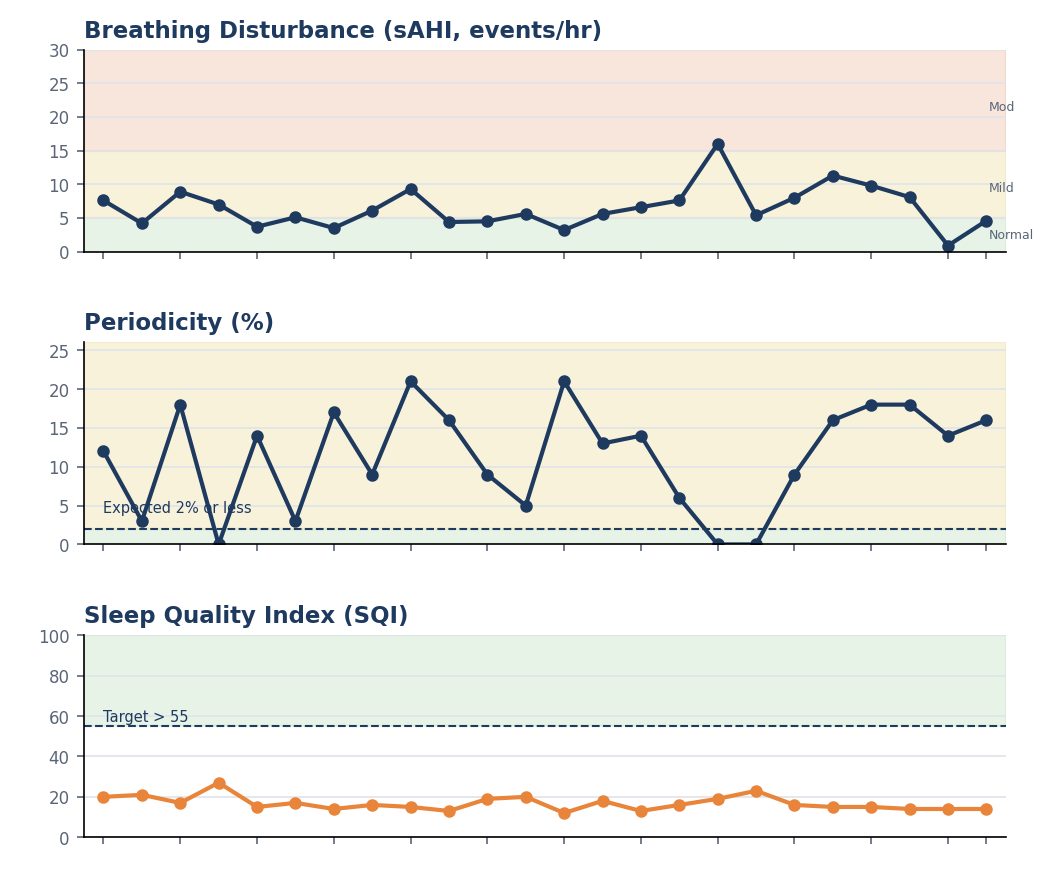
Breathing largely in range; periodicity and sleep quality out of range on every night. The two halves of the record point in different directions.
What it changed. The record said the sleep problem was not primarily an airway problem, so adjusting the appliance was unlikely to be the answer on its own. The breathing rhythm was the finding sent forward for a closer look. Without the nights, the obvious next move would have been to adjust the appliance.
Case D — twenty-three nights, blood pressure included: comfort decided the setting
The question. An adult whose breathing and oxygen numbers were already near normal before the appliance, compared across baseline, a first setting and a second setting, with a home blood-pressure reading every morning.
What the nights showed. Breathing and oxygen stayed near normal at every setting; on those measures no setting separated from the others. The first setting was rated red every morning. The second was green on seven of nine mornings and came with the longest, most efficient sleep of the record (an average of 5 h 56 m against 4 h 47 m at baseline, no night under five hours). Waking blood pressure averaged 137/91 across the month and did not move with the appliance.
What it changed. The second setting was kept because it was the one the patient could wear and it gave more sleep, at no cost on the breathing measures. The sleep-structure problem the appliance had not touched was named as the next thing to look at. The blood-pressure record, thirty-two mornings taken the same way, went to the patient’s physician: a dentist does not diagnose or treat blood pressure, but a month of consistent readings is exactly what a physician can act on. This is the full report for Case D (PDF).
Why an appliance sometimes does not do the whole job
An oral appliance works by holding the lower jaw forward so the airway behind the tongue stays open. For many people that is the whole answer. When the numbers do not improve as expected, it is usually because something other than jaw position is driving things. This is the list we work through, and none of it is a conclusion about any one person.
Several of these can be sorted out with straightforward measurement rather than guesswork, and some belong to your sleep physician rather than to us. What the nights do is tell everyone which ones are worth chasing.
What VTP™ is not
It is not a diagnosis, and it does not replace a physician-ordered sleep study. Dr. Bishara does not diagnose or treat blood pressure or any medical condition; the reports are written to inform a shared decision with your physician about an appliance and about whether an appliance alone is enough. The four cases above are real records shared with permission, with identifying details removed; they show what the method can find, not what it will find for you.
Where it starts
A conversation, then the ring if it makes sense
No commitment to an appliance, no promise that one is right for you. If you snore, grind, wake unrefreshed or gave up on CPAP, the first step is a short conversation about what you are noticing.
Request a call-backReferring physicians: how we co-manage and what you receive.